

 Complete hospital ERP (HIS/HIMS) you own
Stop Adjusting
to Software.
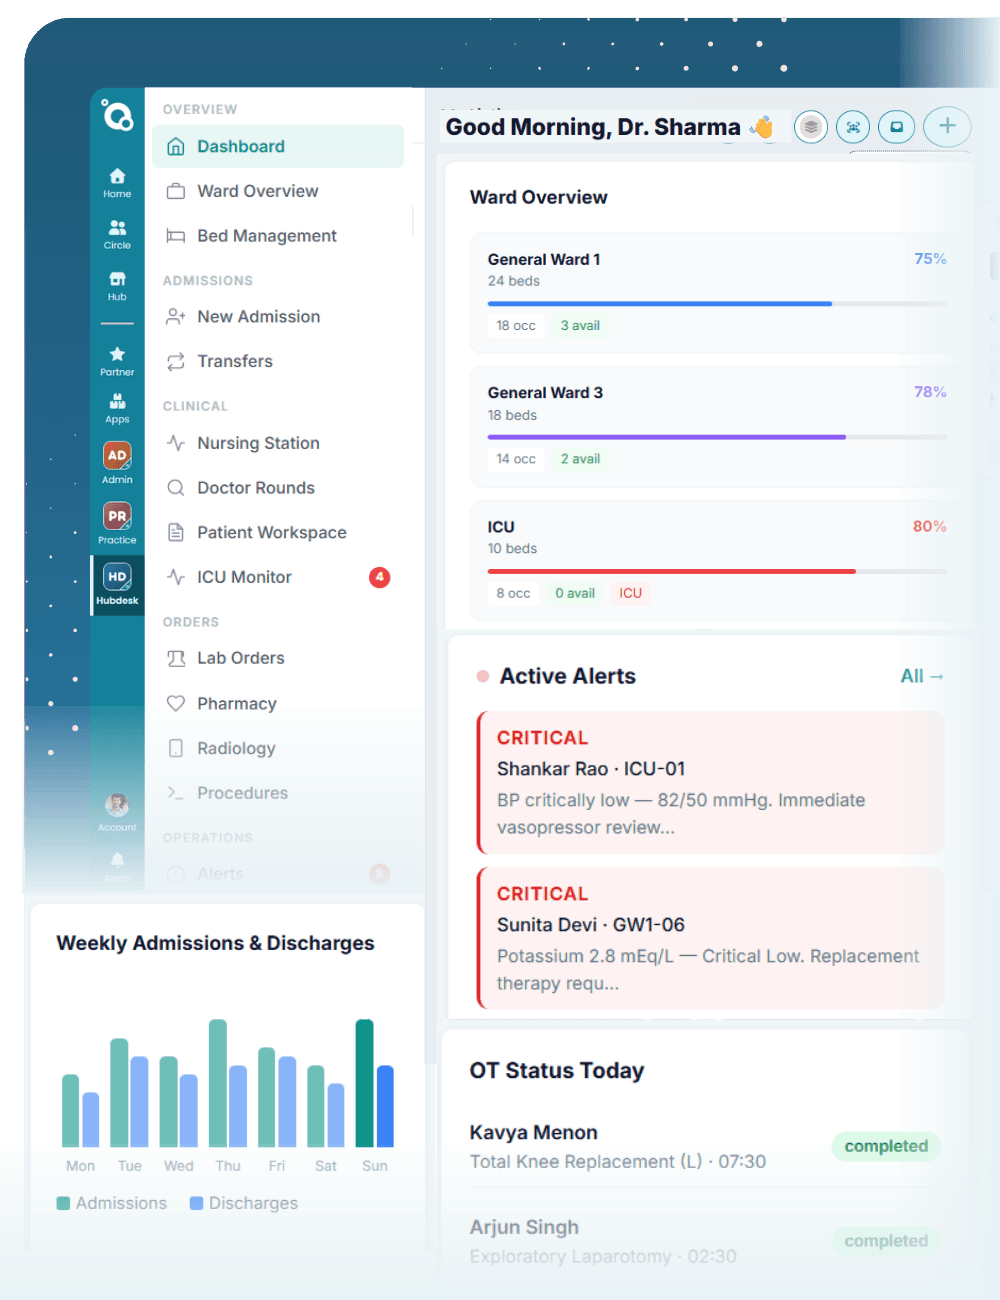
Hospital management software (HIS/HIMS) built around how your hospital already runs. OPD, wards, OT, pharmacy, lab and the billing counter work in one hospital ERP, with your lab analysers, X-ray machines and DICOM imaging connected. You keep the source code, so the money you spend on software stays on your books as an asset instead of going out as a bill every month.
A permanent capital asset, with no recurring operating expense
Grows in value as your team and your data build on it
No licence fee and no renewal to negotiate every year
Our team stays on call for every change that comes after go-live


18+
Modules
Every department
8–16
Weeks
Average go-live
100%
Source Code
Delivered to you
6 Mo
Code Warranty
Post-delivery
$0
After Delivery
No recurring fees
99.9%
Uptime SLA
Cloud hosted

Hospitals running My Hospital
Sre Eswar Hospital, Krishnagiri
A multispeciality hospital with 24/7 emergency care in Krishnagiri, Tamil Nadu, running its hospital management system on My Hospital by Lukenote.
A Question Worth Asking
How much have you paid for your HMS, and what do you own today?
Add it up: the monthly fees, the price rise every year, the enhancement charge each time a process changed. Now suppose you stopped paying tomorrow. What would you walk away with?
You make the compromise.
The software does not quite match how your wards and billing counter work. Someone says the staff can work around it, so they do. It seems small, and you tell yourself it is temporary.
You feel it for the first time.
A new billing rule comes in, or the lab wants its reports in a different format. You raise a ticket and get back a timeline and a quote. You pay it and move on, but now you know where the ceiling is.
Someone suggests switching. The room goes quiet.
At a board meeting, someone asks whether it is time to move to something better. Someone else mentions migrating years of patient records. The discussion ends there and the contract is renewed again, because leaving looks impossible.
You have stopped asking.
The change requests that matter no longer get raised. The workarounds are just how things are done now. When the renewal arrives you sign it without negotiating, out of tiredness more than satisfaction. By then you are locked in.
The way out
Owning the code is what gets you out
A cheaper vendor or a longer contract leaves you in the same place, because someone else still owns the code. When your hospital owns it, the story above cannot play out.
| What matters | My Hospital (you own the code) | Rented HMS (no code ownership) |
|---|---|---|
| Cost over time | One payment, then nothing recurring. | Fees that keep coming every month. |
| Making a change | Your developers change the code. | Raise a ticket, wait, then pay. |
| Your data | Yours, and you can move it anywhere. | On their servers, in their schema. |
| Vendor shuts down | Change the vendor and keep the system. | You lose everything. |
| Team grows | No extra charge for new users. | Per-user fees go up. |
| Regulation changes | Your team handles it. | You wait for their roadmap. |
| Who can maintain it | Any developer you choose to hire. | Only their developers. |
| Price next year | Fixed when you sign, and it stays fixed. | Goes up, and you cannot push back. |
| At year 10 | Everything: the codebase, the data and the logic, a permanent asset on your books. | Nothing. The system stops when the relationship does. |
No Surprises
A hospital ERP you have seen, approved
and own, before you rely on it.
At each step you see the work and approve it before anyone asks you to depend on it.
Free Consultation
We spend time learning how your hospital runs: the departments, the patient flow, the billing structure, and how your teams get through a busy OPD morning. There is no sales pitch and no commitment at this stage. We mostly listen.
No obligation to proceed.
The conversation is free, our assessment is honest, and the decision stays with you.
Scope & Contract
We put in writing exactly what gets built, what it costs and when it is delivered, all fixed before work starts. You sign only when you are happy with it, so the invoice never holds a surprise.
Mock Screens for You to Review & Approve
Before any code is written, your billing, nursing and admin teams see every screen and workflow. They ask for changes and sign off, and we build only what was approved.
Delivery with Full Source Code
We build and test the system, then hand it over working, with the entire codebase. Every layer is documented and every module is yours to keep.
Data Migration
Patient history, masters, pharmacy stock, lab data and financial records are moved across and checked before your staff log in for the first time.
Training
Billing, clinical, admin and management staff each learn their own workflow, one role at a time.
Parallel Run
For one week, old and new run side by side. Every transaction is checked before the old system is switched off.
Go-Live
We are on site on day one, and nothing goes live until every department head says they are ready.
100% Warranty, and We Stay Accountable
Every issue after delivery is ours to fix, with no extra billing and no ticket left open. We answer for the quality of what we build for as long as your hospital runs it.
Request Free Consultation
Tell us about your hospital. We will get back within one business day.
Built for Every Role in Your Hospital
What the day looks like
for each person in your hospital.
A billing clerk, a ward nurse and a surgeon need very different things from the same hospital management system. Here is how My Hospital fits into each of their days, shaped around how they already work instead of how a generic HMS expects them to.
Patient
Fewer counters to stand at, and reports on their phone.
They book an appointment from their phone at midnight without calling anyone. At the front desk, reception already has their name and the reason for the visit. After the consultation, the prescription and the next appointment are on their phone, and test results arrive as soon as they are ready. There are no forms to fill in twice and no reports to chase by phone.
Books an appointment without calling the hospital
Arrives at a reception desk that already has their details
Gets the prescription, reports and discharge summary on their phone
Sees their full history through the patient portal
Why Trust Our Team
We have been inside enough hospitals to know what no one says out loud.
We have stood at billing counters, nursing stations and pharmacy counters and mapped the exact moments where a hospital loses money, misses a charge or fails an audit, and where good staff end up working around bad software.
The billing desk gets calls at 11pm about an OT charge that should have been captured at discharge.
The finance head has a personal Excel file because the system's reports don't match the bank.
The doctor seeing 40 patients a day cannot afford a 3-click prescription workflow.
The nurse knows which items the system won't capture, so she keeps a paper list in her pocket.
The pharmacy counter runs out of a drug because no one saw the alert in time.
The TPA rejection arrives six weeks after discharge with a reason no one can trace back.
The new specialty opened three months ago. The billing module still doesn't reflect it.
The management report for Monday's board meeting was compiled manually over the weekend.
If you recognised a few of these, that is the reason we build the way we do.
Deployment
Your hospital. Your infrastructure.
Your choice.
You get the same system either way, set up for your hospital. What changes is where the servers sit.
Recommended for most hospitals
Cloud Hosted
Your hospital management system, hosted and run by us. You go live in days without buying a single server. We take the backups and watch the uptime, and your staff log in from any device, at the nursing station or from home.
- No hardware to buy, running within days
- 99.9% uptime with daily managed backups
- Works on any device, wherever your staff are
- Updates applied by us, nothing to install
For data sovereignty and compliance
On Your Premises
The complete hospital information system runs inside your own network. Patient records, EMR data and billing history never leave your premises. Government hospitals, multi-specialty groups and anyone with strict data residency rules usually choose this.
- Complete data sovereignty: nothing leaves the building
- Keeps running on the local network when the internet drops
- No monthly hosting bill
- Full control for regulated and government hospitals
Our Promise
A team that picks up the phone
for as long as you run this hospital.
After handover, the people who built your system stay reachable, and they already know how your hospital works.
100% Code Warranty for 6 Months.
Every module, workflow and screen we deliver is fully covered for six months after delivery. If anything within the project scope does not behave as agreed, we fix it, with no questions asked and no extra bill. You will not be left with a support ticket nobody answers. We wrote the code, and we stand behind it.
Covers everything within the agreed project scope. Applies from the day of final delivery handover.
We stay with you after delivery.
A new government scheme, a new insurance partner, a new specialty, a second branch. Every hospital goes through these sooner or later. Our team stays available for each one for as long as you operate. You call us and we handle it.
Our name is on it too.
The system we build carries our name next to yours, so we want it working at year three, year five and year ten as much as on launch day. That is why every engagement is set up for you to own the software, with no recurring dependency on us.
What is My Hospital by Lukenote?
My Hospital is a complete hospital ERP and hospital management system (HIS/HIMS) from Lukenote (Emitlogic Technologies). It is built around how your hospital already works, and the hospital owns it, with no licence renewals or per-user fees. OPD, IPD and the operation theatre, pharmacy, stores, laboratory, radiology, billing and insurance, HR and payroll, finance and MIS all run as one system. It connects to lab analysers, X-ray and imaging equipment (DICOM/PACS), biometric devices and accounting, and runs in the cloud or on-premise.
One complete hospital ERP: every department, one system
Many hospitals end up with a billing package, a separate lab system, a pharmacy program and a spreadsheet for HR, and the numbers never quite agree. Shopping for HMS software or HIS software usually starts there. My Hospital replaces the pile with one system that is also your hospital administration software, OPD management software and hospital inventory management software for stores and pharmacy. Here a patient is one record from registration to discharge. Every department works from the same information, and management sees the whole hospital in one place.
- OPD, IPD, beds and the operation theatre
- Pharmacy, stores and purchase
- Laboratory and radiology
- Billing, insurance, TPA and government schemes
- HR, payroll and attendance
- Finance, accounts and MIS
What is a hospital ERP, HIS or HIMS?
A hospital ERP, hospital information system (HIS) or hospital information management system (HIMS) is the software a hospital runs on, covering clinical, operational and financial work in one place. People use the names interchangeably. What matters is whether it fits the way your hospital works, and whether you own it.
Results and images where doctors need them: analysers, X-ray and DICOM/PACS
Lab analysers send results straight into the patient's record. X-ray, CT and other imaging equipment send DICOM images through PACS to the doctor's screen. Nobody waits for films, retypes values or sends a runner between departments, and the consultant can decide at the bedside.
Every charge captured, every claim paid: billing, insurance and TPA
This is hospital billing software built into the same system as the wards. Charges are recorded where care happens, on the ward, in the theatre, at the pharmacy counter, instead of being pieced together on discharge day. Insurance, TPA and government-scheme claims (such as PMJAY in India) go out right the first time, so fewer come back rejected weeks later and less revenue quietly goes missing.
Staff paid right, rosters that work: hospital HRMS and payroll
Biometric attendance feeds rosters and payroll, and statutory deductions are handled. Staff are paid correctly and on time, which counts for a lot when a good nurse has offers from other hospitals.
Numbers you can trust: finance, accounts and MIS
Finance sees the same numbers as the wards. Accounts flow into your accounting system (such as Tally or SAP), and MIS reports are ready when the management meeting comes round, not weeks later.
Software that fits your hospital, owned by you
Your staff stop working around the software. The system is built around how your hospital works, and the code, data and logic become the hospital's permanent asset. There are no licence renewals, no per-user fees and no enhancement charge each time a process changes.
Your data, your choice: cloud or on-premise
Run My Hospital in the cloud or on your own servers, whichever your IT policy and internet connection call for. Trust, government and private hospitals can each pick the model that suits them.
Who uses My Hospital
Multi-specialty hospitals
Every department working from one record.
Nursing homes and small hospitals
A complete ERP without per-user fees.
Trust and government hospitals
On your own servers, with code you own.
Hospital groups
One system you own, across every facility.
Common questions
What hospitals ask us before they buy
Choosing a hospital management system is a big decision, and you will live with it for years. These are the questions owners, administrators and IT heads ask us most often.
Is My Hospital a complete hospital ERP? What does it include?
Do we actually get the complete source code? What does the code handover include?
How does Lukenote customize the HIS for our hospital’s specific workflows?
How is this different from a SaaS hospital software subscription?
Does My Hospital support both on-premise and cloud deployment?
Can the hospital software handle insurance and TPA billing?
How does the hospital management system handle HRMS, payroll, and staff scheduling?
How long does hospital software implementation take, and what happens at each stage?
Can the HIS integrate with our existing PACS, lab equipment, biometric devices, or accounting software?
Is the hospital software suitable for multi-location hospital groups or chains?
What ongoing support do we get after the system goes live and code is handed over?
Start the conversation
New TPA next quarter? A regulation next month? Call us, and we will handle it.
Our team will visit your hospital, map your workflows and send a detailed proposal with a fixed project cost. No recurring fees, the complete source code included, and no obligation to go ahead.